


YOUR CART
- No products in the cart.
Subtotal:
$0.00
BEST SELLING PRODUCTS



In the rapidly evolving landscapes of biohacking, wellness, and anti-aging medicine, terms like peptides and steroids are frequently grouped together. Both categories contain compounds used to enhance athletic performance, accelerate muscle recovery, promote fat loss, and combat age-related decline.
However, despite these overlapping outcomes, classifying them under the same umbrella is a fundamental misconception. Are peptides considered steroids? The direct short answer is no. Peptides and steroids belong to entirely different chemical families, interact with the human body through completely different biological pathways, and carry starkly different regulatory and safety profiles.
Understanding the distinction between peptides vs steroids is essential for patients, athletes, and fitness enthusiasts navigating performance-enhancing options, anti-aging therapies, or regenerative medicine in the United States.
To grasp why peptides are not anabolic steroids, it helps to examine their foundational chemical structures.
       [ PEPTIDES ]                          [ STEROIDS ]
Short chains of Amino Acids          Four fused Carbon Rings (Sterane Core)
      (Protein Fragments)                      (Lipid-based)
               │                                     │
               ▼                                     ▼
 Binds to Surface Receptors            Passes Cell Membranes Directly
 (Triggers Cascade Signals)            (Binds to Nuclear Receptors)
               │                                     │
               ▼                                     ▼
  Stimulates Natural Secretion         Replaces/Suppresses Natural Hormones
Peptides are short chains of amino acids—the fundamental building blocks of proteins—linked together by peptide bonds. By scientific definition, a molecule containing between 2 and 50 amino acids is classified as a peptide. Once a chain exceeds 50 amino acids, it is generally considered a full protein (such as insulin or human growth hormone).
In the body, peptides function primary as cellular messengers. They attach to specific receptors on the surface of target cells, transmitting instructions to stimulate, inhibit, or regulate various physiological processes. Common examples include:
Steroids are lipid-based compounds characterized by a specific core structure consisting of four fused carbon rings (the cyclopentanoperhydrophenanthrene skeleton). Unlike peptides, steroids are not made of amino acids; they are derived from cholesterol.
The steroid family is diverse, including:
The distinction between peptide hormones vs steroid hormones comes down to solubility and receptor interaction:
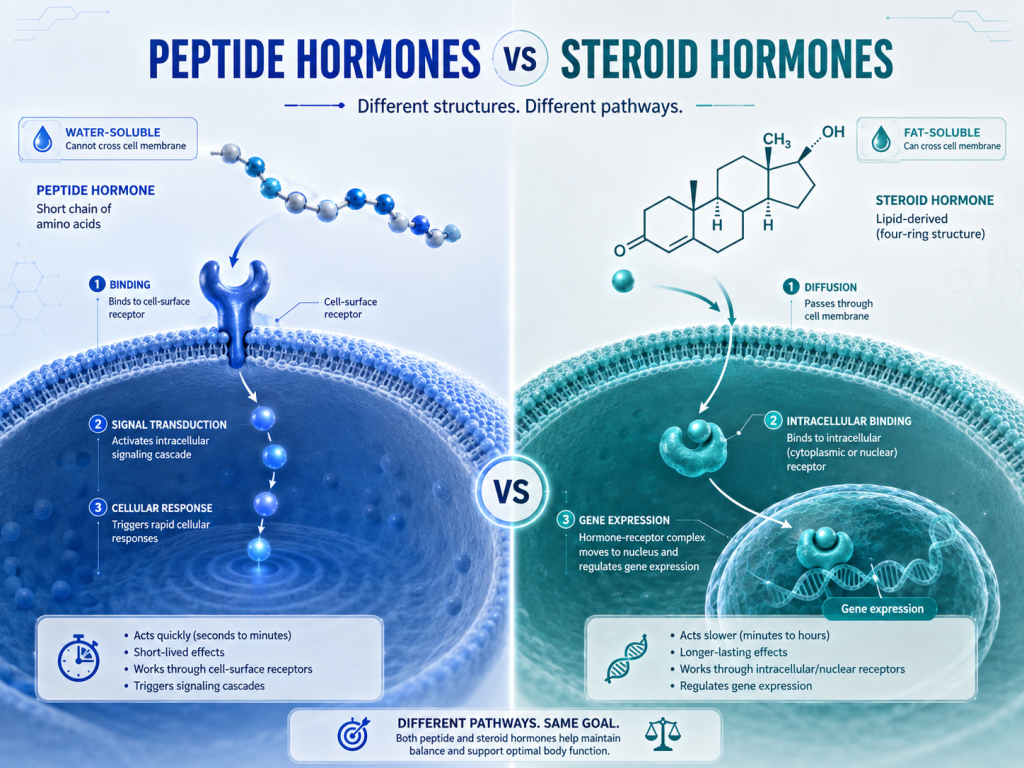
When analyzing the difference between peptides and steroids, the crucial operational distinction lies in whether a compound stimulates natural production or replaces it.
┌────────────────────────────────────────────────────────────────────────┐
│                        MECHANISM OF ACTION                             │
├────────────────────────────────────────────────────────────────────────┤
│ PEPTIDES:                                                              │
│ [Peptide Signal] ──> [Pituitary/Target Gland] ──> [Natural Hormone Output] │
│ *Works within body's natural feedback loops (Pulses/Gated)             │
│                                                                        │
│ STEROIDS:                                                              │
│ [Exogenous Steroid] ──> Direct Cellular Binding ──> High Anabolic State │
│         │                                                              │
│         └──> Negative Feedback Loop ──> [Natural Production Shut Down] │
└────────────────────────────────────────────────────────────────────────┘
Peptides work via signaling cascades. When you administer a peptide secretagogue like Ipamorelin, the peptide does not replace growth hormone in your bloodstream. Instead, it instructs your pituitary gland to release its own stored growth hormone in natural, physiological pulses.
Anabolic steroids operate far more aggressively. When exogenous testosterone, trenbolone, or nandrolone enters the body, it directly floods androgen receptors across muscle, bone, and neural tissue.
One of the defining risks of anabolic steroids is the suppression of the Hypothalamic-Pituitary-Gonadal (HPG) axis. Because the body detects massive exogenous levels of hormones, it triggers a negative feedback loop, shutting down endogenous testosterone production and causing testicular atrophy. Users typically require Post-Cycle Therapy (PCT) to restart natural hormone production.
Peptides rarely cause complete endocrine shutdown. Because growth hormone secretagogues work with the body's natural negative feedback mechanisms, pituitary secretion remains regulated, minimizing the risk of permanent organ suppression.
Are peptides anabolic steroids? Absolute not. While some peptides exhibit anabolic (tissue-building) downstream effects—such as increasing IGF-1 or elevating human growth hormone—they lack the steroid carbon structure and do not bind to androgen receptors. They are functionally, chemically, and biologically distinct from anabolic-androgenic steroids.
To clearly see how these two therapeutic classes compare side-by-side:
| Feature | Peptides | Anabolic Steroids |
| Chemical Structure | Short chains of amino acids (2–50) | Four-ring carbon lipid core (Cholesterol-based) |
| Primary Mechanism | Binds cell-surface receptors to signal natural release | Diffuses into cells to alter gene transcription directly |
| Receptor Targets | G-protein coupled receptors, growth factor receptors | Androgen receptors (AR) |
| Endogenous Production Impact | Preserves or gently stimulates natural pathways | Suppresses or completely shuts down HPG axis |
| Anabolic Potency | Moderate, gradual, highly targeted | High, rapid, systemic muscle growth |
| Organ Toxicity | Extremely low (No liver/kidney strain) | Moderate to High (Hepatotoxicity with oral AAS, cardiovascular strain) |
| Route of Administration | Subcutaneous injection, nasal sprays, oral pills | Intramuscular injection, oral tablets, transdermal gels |
| DEA Schedule (US) | Non-scheduled (Legend drugs / RX required) | Schedule III Controlled Substances |
| WADA / Anti-Doping Status | Prohibited under S2 (Peptide Hormones & Growth Factors) | Prohibited under S1 (Anabolic Agents) |

Medical practitioners in the US utilize peptide therapy vs steroids for vastly different clinical outcomes.
      PEPTIDE THERAPY                         ANABOLIC STEROIDS
  ┌───────────────────────┐               ┌───────────────────────┐
  │ • Tissue Repair       │               │ • Severe Muscle Loss  │
  │ • Fat Metabolism      │               │ • Hypogonadism (TRT)  │
  │ • Collagen Production │               │ • Delayed Puberty     │
  │ • Anti-Aging / GH     │               │ • Rapid Hypertrophy   │
  └───────────────────────┘               └───────────────────────┘
In anti-aging medicine across the US, peptide therapy has largely superseded harsh hormonal replacement strategies for general rejuvenation. Peptides allow physicians to optimize metabolic function, sleep quality, skin elasticity, and immune health with minimal disruption to the patient's baseline biology.
The question "are peptides legal in the US?" involves a nuanced legal framework enforced by the FDA, DEA, and sports regulatory agencies like USADA.
| Category | Regulatory Body | Legal Status in the US | Prescription Needed? | Common Classification |
| Prescription Peptides | FDA | Fully Legal for medical use | Yes | FDA-Approved Drug / Compoundable |
| Research Peptides | FDA / FTC | Gray Market (Not for human consumption) | No (Sold for research) | Unapproved New Drug |
| Anabolic Steroids | DEA / FDA | Fully Legal ONLY with strict prescription | Yes | Schedule III Controlled Substance |
| Compounded Peptides | FDA (503A/503B) | Restricted under FDA Category 1/2 lists | Yes | Prescription Pharmaceutical |
| Peptides in Sports | WADA / USADA | Banned in competitive athletics | N/A | Prohibited Substance (S2 Category) |
Navigating the US legal landscape requires distinguishing between controlled substances, FDA-approved therapeutics, and research compounds.

Are peptides legal in the US? Yes, provided they are prescribed by a licensed healthcare provider and sourced through regulated channels.
Under the Anabolic Steroids Control Act of 1990 (and expanded in 2004), anabolic steroids are classified as Schedule III Controlled Substances in the United States. Unlawful possession, distribution, or possession without a valid medical prescription is a federal offense carrying severe criminal penalties.
Peptides are not controlled substances under the Controlled Substances Act (CSA). While selling unapproved peptides for human consumption violates FDA regulations, mere possession of non-scheduled peptides does not carry the criminal charges associated with Schedule III anabolic steroids.
While many peptides are legal for medical prescription in the US, they are strictly prohibited in tested athletics. The World Anti-Doping Agency (WADA) and the United States Anti-Doping Agency (USADA) list both anabolic steroids (Section S1) and peptide hormones/growth factors (Section S2) on their Prohibited List. Athletes using peptides like CJC-1295, BPC-157, or GHRPs risk suspension and bans.
Because peptides and steroids act via different pathways, their safety profiles diverge significantly.
┌────────────────────────────────────────────────────────────────────────┐
│                        SIDE EFFECT COMPARISON                          │
├────────────────────────────────────────────────────────────────────────┤
│ ANABOLIC STEROIDS (Systemic Strain):                                   │
│  ├── Cardiovascular: Hypertension, altered lipid profiles (HDL/LDL)    │
│  ├── Endocrine: Testicular atrophy, gynecomastia, HPTA shutdown        │
│  └── Hepatic/Dermal: Liver toxicity (orals), severe acne, hair loss   │
│                                                                        │
│ PEPTIDE THERAPY (Mild / Localized):                                    │
│  ├── Injection Site: Mild redness, itching, localized irritation      │
│  ├── Transient Effects: Water retention, increased appetite, flushing │
│  └── Long-Term: Requires monitoring for insulin sensitivity (GH-types) │
└────────────────────────────────────────────────────────────────────────┘
Anabolic steroids produce significant systemic strain due to androgen receptor saturation throughout the body:
Peptides generally present a far milder side effect profile because they act via targeted receptor pathways:
No, peptides and steroids are chemically and biologically different. Peptides are amino acid chains that signal natural body processes, while steroids are cholesterol-based lipids that directly bind to androgen receptors to manipulate gene expression.
Standard employment drug screens in the US do not test for peptides or anabolic steroids; they typically screen for narcotics, amphetamines, THC, and benzodiazepines. However, sports anti-doping tests (USADA/WADA) explicitly test for both peptides and anabolic steroids using advanced mass spectrometry.
Peptides cannot directly replace testosterone if a patient has primary hypogonadism (testicular failure). However, for individuals with secondary hypogonadism or those seeking to optimize hormone levels naturally, gonadotropin-releasing peptides (like hCG or Kisspeptin) or growth hormone secretagogues can stimulate the body's natural hormone production pathways without causing fertility loss or organ shutdown.
Yes, to legally obtain peptides intended for human therapeutic use in the US, you must receive a evaluation and prescription from a licensed healthcare provider, fulfilled through a regulated pharmacy.
Although peptides and anabolic steroids are frequently conflated due to their popularity in fitness, regenerative health, and anti-aging circles, they are fundamentally distinct compound classes. Steroids operate as powerful, lipid-based hormone replacements that directly bind to intracellular androgen receptors, carrying significant risks of systemic shutdown and organ strain. In contrast, peptides function as precise amino acid messengers that prompt the body's natural systems to optimize healing, metabolic output, and hormone release.









